

Medical experts in the United States have broadened their recommendations for who should receive migraine prevention therapy and which preventive drugs to prescribe. A panel of specialists systematically reviewed the available evidence and issued key updates to a 2012 joint guideline from the American Academy of Neurology (AAN) and the American Headache Society (AHS). The new recommendations appear in a special article in the journal Headache and are endorsed by the American Academy of Family Physicians.
Why the Guidelines Changed

“Migraine is the most common reason for people to see a neurologist, and is encountered even more commonly in primary care settings,” explains AHS president and neurologist Matthew Robbins of Weill Cornell Medicine. “Newer treatment options have revolutionized the care for millions of people in the US and worldwide.”
The updated guidance aims to make it easier for patients with debilitating headaches or migraines to receive effective preventive treatments—even if they do not strictly meet the definition of chronic migraine. Chronic migraine is characterized by headaches occurring more than 15 days per month for over three months, with at least eight of those days involving migraine features such as throbbing on one side of the head, nausea, or sensitivity to light and sound.
Previously, preventive treatment was often reserved for those with frequent attacks. Now, the guideline authors argue that more patients could benefit, even if their migraine frequency is lower.
Who Should Now Receive Preventive Treatment?
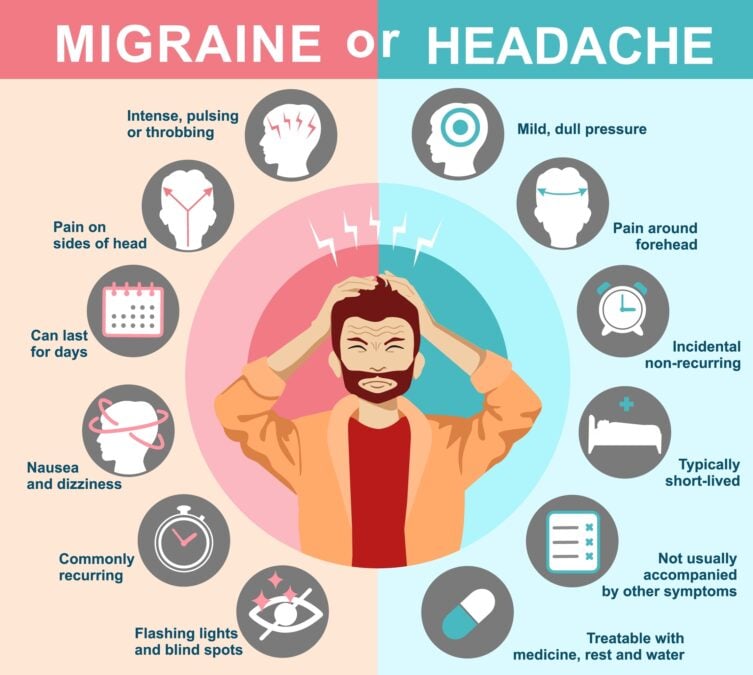
According to the updated guidelines, clinicians in the US should offer preventive treatment to patients who experience four or more moderate-to-severe headache days or migraine attacks per month, or who have substantial migraine-related disability. This change reflects the eligibility criteria used in many clinical trials for migraine prevention, which often require only four or more migraines monthly.
“Preventative treatments may prevent the transition from episodic to chronic migraine,” the guideline authors note. Studies have shown that the frequency of episodic headaches per month is a key predictor of progression to chronic migraine.
The recommendations are not legally binding, but AAN president Natalia Rost, a neurologist at Massachusetts General Hospital, calls them “an important resource for neurologists and other clinicians working to provide the best possible care.”
Expanded Access to Newer Medications
Under the new guidelines, people with migraine attacks or severe headaches should have broader access to newer treatments, including CGRP-targeting drugs—the first medications developed specifically for migraine prevention. Atogepant, erenumab, fremanezumab, galcanezumab, and eptinezumab are now recommended as first-line pharmaceutical options. These come in different forms: one is a daily tablet, one is an infusion, and the rest are injections. In clinical trials, they have shown some of the strongest evidence of efficacy for preventing migraine attacks.
For those with chronic migraine, Botox (onabotulinumtoxinA) is also now recommended. It was not included in the 2012 guidelines but was recommended by the AAN for headaches in 2016.
Finding the Right Treatment
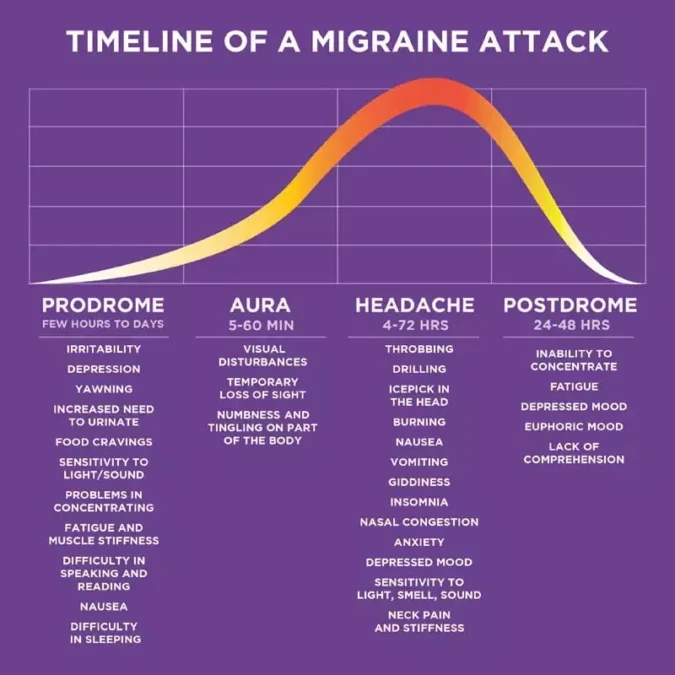
Because migraine patients respond differently to preventive treatments, finding the right medication can involve trial and error. “The research shows many different types of medications may be effective for preventing migraine attacks and reducing symptoms,” says guideline author and headache medicine specialist Rebecca Burch of the University of Vermont. “The guideline includes recommendations for both previously established and newer medications. If one type of medication is not working well, a different type may still be effective. It is important for clinicians and patients to know that there are many options.”
Recommended Medications by Migraine Type
The 2026 guidelines break down the most effective treatments for episodic and chronic cases:
- Episodic migraine: Atogepant, eptinezumab, erenumab, fremanezumab, galcanezumab, propranolol, topiramate, and valproate have the best evidence of high efficacy.
- Chronic migraine: The same drugs (except propranolol) are suggested, with Botox as an additional option.
The authors also detail which medications have the most side effects or possible long-term or unknown harms. For patients with both fibromyalgia and migraine, the guidelines recommend amitriptyline.
Medication Overuse and Long-Term Management

The guidelines also address medication overuse. “The use of medications to treat acute migraine attacks too frequently is termed ‘medication overuse’,” the authors write. “The frequent use of medications to treat acute migraine attacks is one indication that preventive treatment should be offered or optimized.”
Migraine is a lifelong disorder that fluctuates in frequency, severity, and duration, the guidelines explain. After six months of preventive treatment, clinicians should discuss the potential benefits and risks of tapering, including the possibility that migraine attacks may become more frequent after stopping medication—though evidence on this is limited.
“There are a variety of effective preventive medications that work in different ways, including newer classes of medications that have been released in the past several years,” says guideline author and neurologist Tamara Pringsheim from the University of Calgary in Canada. “For people experiencing frequent migraine attacks or attacks that affect the ability to function normally, this guideline can help clinicians determine which preventive medications may be able to help.”
The guidelines are published in Headache.






